
Jaundice can change the atmosphere around a gallbladder cancer diagnosis almost overnight. The eyes turn yellow, urine becomes darker, itching may become difficult to ignore, and blood tests show that bilirubin is rising. Families often take this as a sign that the cancer must have progressed too far for surgery.
Jaundice certainly deserves careful attention, but it does not decide operability on its own.
Gallbladder cancer can obstruct the channels that carry bile from the liver into the intestine. Whether surgery remains possible depends on what is causing that obstruction, how far the tumour has extended, whether important blood vessels or bile ducts are involved, whether cancer is present elsewhere, and whether the disease can reasonably be removed completely.
Patients preparing for a specialist review may also benefit from understanding how gallbladder cancer is assessed and treated before discussing their own CT or MRI findings.
No. Jaundice does not automatically make gallbladder cancer inoperable. It often means that bile drainage has become obstructed and may indicate more locally advanced disease, but the surgical decision still depends on imaging, staging, anatomy and whether complete tumour removal appears feasible.
A surgical review usually needs to establish:
That is why a bilirubin result, even when very high, cannot answer the surgical question by itself.
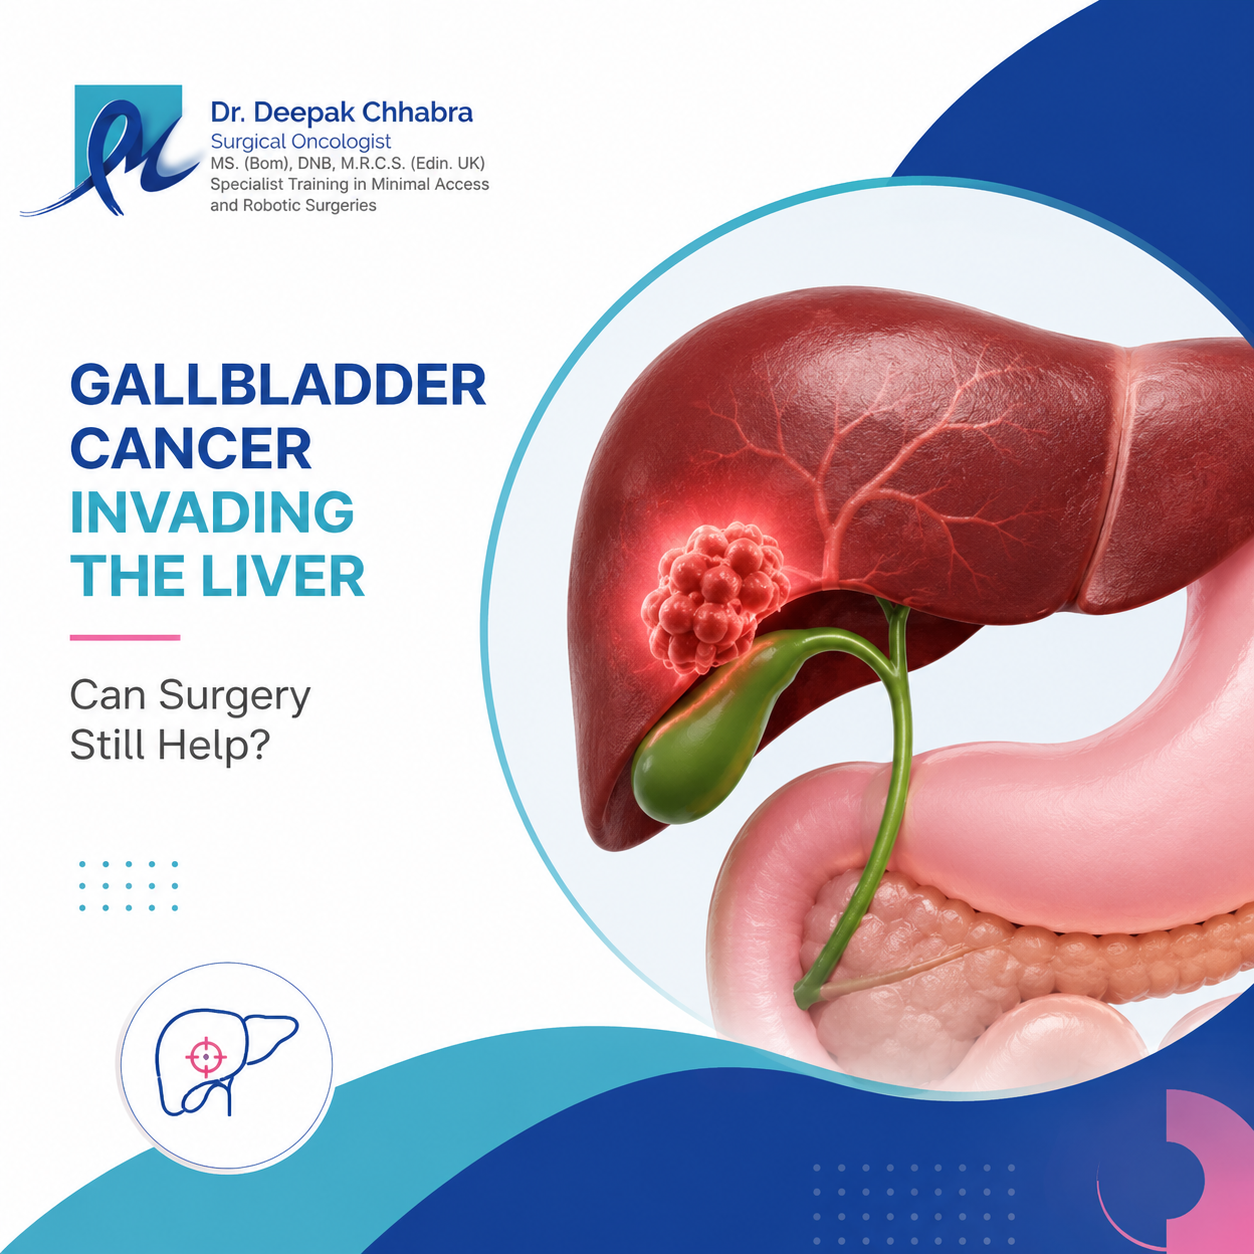
The gallbladder sits directly beneath the liver and close to the main bile ducts. Bile produced by the liver normally travels through these ducts before reaching the intestine.
A gallbladder tumour growing toward the neck of the gallbladder, liver hilum or nearby biliary structures can narrow or block that pathway. When bile cannot drain normally, bilirubin builds up in the bloodstream.
Patients may notice:
The National Cancer Institute explains that gallbladder cancer can narrow or block the bile ducts, slowing bile flow and causing jaundice.
What matters next is why the blockage has occurred and what the surrounding anatomy looks like.
Two patients can have obvious jaundice and still have quite different scan findings.
A scan report may use phrases such as biliary obstruction, intrahepatic biliary dilatation or hilar involvement. Those terms sound technical because they describe anatomy that is technically demanding.
For a surgeon, the important issue is not simply that a duct is blocked.
The team needs to understand:
These details can completely change the operation being considered.
A short radiology sentence may therefore be useful, but it rarely replaces review of the actual contrast-enhanced CT or MRI images when major gallbladder cancer surgery is being assessed.
Jaundice tells us that bile is not draining normally, but it does not tell us the full stage of the cancer.
In one patient, the blockage may be caused by the tumour growing into or pressing on the nearby bile ducts. In another, the disease may be more extensive. The yellowing of the eyes can look the same in both situations, even though the treatment plan may be very different.
This is why doctors look beyond the symptom itself. CT or MRI findings, lymph nodes, involvement of nearby structures and evidence of spread elsewhere all help determine the actual stage and whether surgery should still be considered.
So jaundice should be taken seriously, but it should not be treated as a final answer about operability.
For someone being assessed for surgery, imaging needs to provide much more information than the size of the gallbladder mass.
The gallbladder lies against the liver, so direct extension into adjacent liver tissue is possible. Surgeons need to understand how much liver is involved and what would need to be removed with the gallbladder.
The extent of tumour along the biliary system can strongly influence resectability and surgical complexity.
The portal vein and hepatic arterial structures are close to this region. Their relationship to the tumour may affect what can safely and completely be removed.
Suspicious regional or more distant lymph nodes can influence staging and treatment planning.
The chest and abdomen are assessed for evidence that cancer has spread beyond the primary area.
The American Cancer Society describes gallbladder cancer as resectable when the treating team believes it can be removed completely, based on imaging and other assessment; disease that has spread too far or cannot be completely removed is considered unresectable.
This is the distinction patients should focus on—not jaundice alone.
Saying that jaundice does not automatically rule out surgery should not be confused with saying that jaundice is unimportant.
When gallbladder cancer is causing biliary obstruction, the tumour may be involving anatomy that makes treatment substantially more complicated than a routine gallbladder operation.
Selected cancer operations may require removal of the gallbladder together with adjacent liver tissue and regional lymph nodes. Bile-duct resection or additional procedures may be required in particular anatomical situations.
What is appropriate varies considerably from one patient to another.
This is where specialist interpretation matters. The issue is no longer simply whether the gallbladder can be removed. The surgeon has to judge whether an oncologically complete operation is possible without leaving the patient with inadequate liver function or unacceptable surgical risk.
Jaundice sometimes needs treatment before the final cancer plan is carried out.
If bile drainage is significantly obstructed, doctors may consider a procedure that allows bile to flow again. Depending on the anatomy, this might involve an endoscopic stent or drainage performed through the liver.
The reason is not always the same.
Drainage may be considered to:
NCI describes endoscopic stenting and percutaneous transhepatic biliary drainage as options for relieving biliary obstruction and notes that drainage may sometimes be considered before surgery in jaundiced patients.
This should remain an individual clinical decision. Not every jaundiced patient automatically needs preoperative drainage.
This causes a surprising amount of confusion.
Some families hear that a stent is needed and conclude that surgery has already been abandoned. Others assume that once bilirubin falls after stenting, the cancer must have become operable.
Neither conclusion is reliable.
A stent treats the obstruction. It does not remove the cancer or determine its anatomical resectability.
A patient may undergo drainage while further surgical assessment continues. In another case, drainage may be used primarily to relieve symptoms when cancer cannot be removed.
The scan and staging explain which situation applies.
There are situations where a major cancer operation is unlikely to provide a reasonable path to complete tumour removal.
Imaging may show extensive involvement of critical structures, disease may be present at distant sites, or the amount of liver and biliary anatomy that would need to be removed may make surgery unsafe.
General health also matters.
A technically imaginable procedure is not necessarily the right operation for every patient. Heart and lung health, liver function, nutrition, performance status and the expected extent of surgery all affect the decision.
This is particularly important in YMYL medical content: resectability cannot responsibly be promised from a symptom, report excerpt or online description.
It requires individual specialist assessment.
Current search behaviour around this condition shows that patients are often looking for more than a diagnosis. They want to know who can interpret a complex scan and explain whether surgery remains realistic.
For someone exploring gallbladder cancer treatment in Mumbai, jaundice is precisely the kind of situation where the quality of surgical assessment matters.
A gallbladder cancer specialist in Mumbai may need to review the tumour’s relationship with the liver, bile ducts and nearby vessels before discussing operability. That review can also clarify whether biliary drainage has a role and whether additional staging is required.
Patients searching for a gallbladder cancer doctor in Mumbai should therefore look beyond a generic cancer label. Experience with hepatobiliary anatomy and surgical oncology is particularly relevant when the tumour is close to the liver hilum or major bile ducts.
As a cancer specialist in Mumbai, Dr. Deepak Chhabra works in surgical oncology with training and clinical focus in hepatopancreatobiliary cancer surgery. For a jaundiced patient, the useful consultation is one that explains the anatomy on the patient’s own images rather than offering a yes-or-no answer based only on bilirubin levels.
A useful surgical consultation starts with the right records.
Bring the actual CT or MRI images, not only the written report. If the patient has already undergone ERCP, stenting or another biliary drainage procedure, carry those records as well.
Recent bilirubin and liver-function results are useful, particularly when they show how values changed before and after drainage.
Also bring any available pathology or biopsy reports, hospital discharge summaries and details of treatment already received.
For this particular problem, a chronological set of records can help the surgeon understand how the jaundice developed and how the anatomy has changed over time.
No, jaundice does not automatically mean stage 4 gallbladder cancer. It can result from local obstruction of the bile ducts, while stage 4 depends on the overall anatomical stage and distant spread. CT or MRI staging and specialist assessment are required to determine the actual stage.
Yes, surgery may still be possible in selected patients with biliary obstruction. The decision depends on the location of the blockage, liver and bile-duct involvement, vascular anatomy, distant spread and whether complete removal appears feasible. The actual cross-sectional images should be reviewed before operability is judged.
No, a biliary stent does not by itself mean surgery has been ruled out. Stents may be used to improve bile drainage and relieve obstruction while further treatment or surgical planning is underway. The purpose of the stent should be interpreted alongside staging and the overall treatment plan.
No, preoperative biliary drainage is not automatically required for every jaundiced patient. Its role depends on the severity and site of obstruction, liver function, infection risk and the proposed treatment strategy. The hepatobiliary and treating teams should decide whether drainage is likely to add benefit in the individual case.
Jaundice is an important development in gallbladder cancer. It tells the treating team that bile flow has been disrupted and that the anatomy needs careful assessment.
What it cannot tell anyone, on its own, is whether surgery is possible.
That judgement comes from the scans: where the tumour has grown, which ducts and blood vessels are involved, whether disease is present elsewhere, and whether a complete operation can be performed while preserving enough healthy liver and acceptable function.
For patients meeting Dr. Deepak Chhabra after developing jaundice, bringing the actual CT or MRI images and records of any stent or drainage procedure can make the consultation far more informative.
The aim is not to offer reassurance for its own sake, nor to assume the worst from one symptom.
It is to determine, as accurately as possible, what the jaundice represents anatomically and what treatment options that anatomy still allows.
Medical Disclaimer:
This article provides general educational information and is not a substitute for personalised diagnosis, staging or treatment advice. Gallbladder cancer operability depends on tumour location and extent, liver and bile-duct involvement, vascular anatomy, lymph-node status, distant spread, liver function, overall health and multidisciplinary assessment. Decisions about biliary drainage, surgery and other treatment should be made by the treating specialist team.

Stay up-to-date with the latest developments in cancer research, treatment, and patient stories through our curated collection of cancer blogs and news articles. From breakthrough discoveries to inspiring survivor journeys.
Discover first hand accounts from patients who have experienced compassionate care and expert treatment at our clinic. Read their reviews to get to know their journey.

5 Out of 5 from 92 Reviews







 VIDEO CONSULTATION
 Phone Calls
 Physical visit